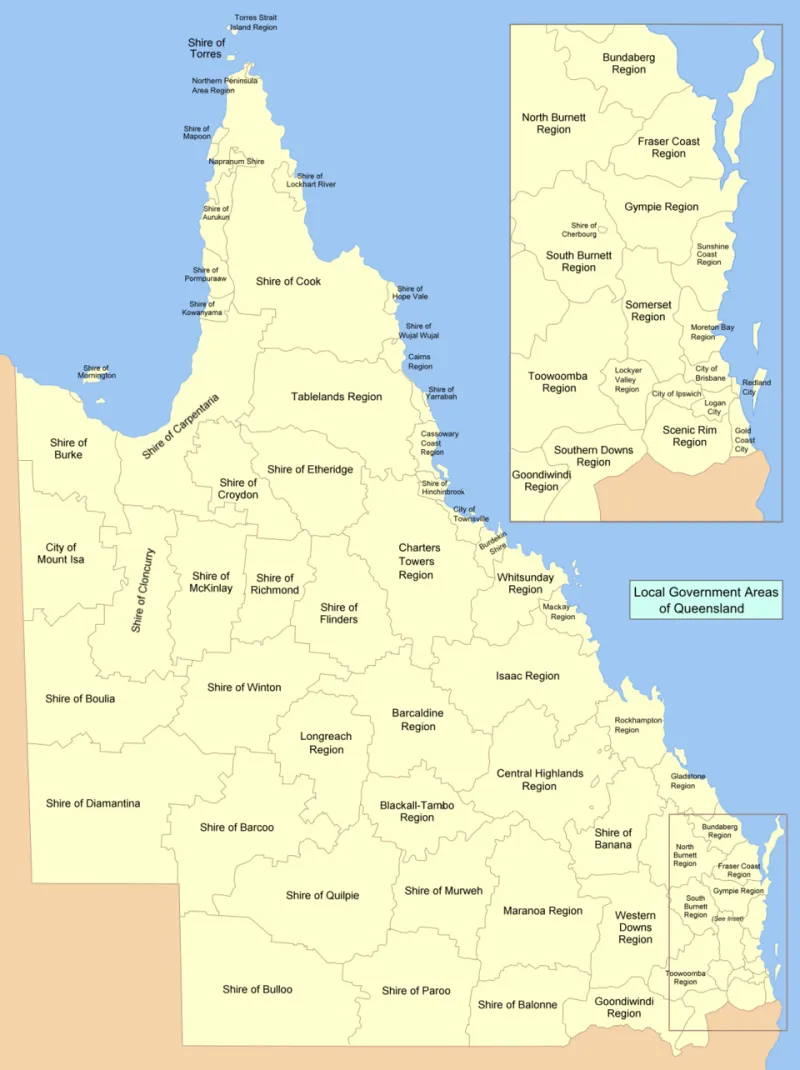
Lost in Translation: Why Queensland's Migrant Communities Are Missing from the Water Fluoridation Conversation
Photo: Oregon National Guard, CC BY 4.0, via Wikimedia Commons
Queensland adds fluoride to the drinking water of most of its urban population. This is, by any measure, one of the state's longest-standing and most evidence-supported public health interventions. Yet for a substantial and growing share of Queenslanders — those who arrived from countries where water fluoridation is uncommon, unheard of, or actively discouraged — the policy exists as an invisible fact, neither explained nor discussed.
The result is a significant information gap: one that affects not just individual health decisions, but the broader public conversation about fluoridation itself.
A Global Patchwork of Water Treatment Practices
Fluoridation is far from universal. While Australia, the United States, Ireland, and New Zealand have long maintained community water fluoridation programs, the practice is absent in most of Europe, much of Asia, and the majority of South and Central America. In many countries, fluoride is added to salt or milk instead — or not added at all.
For someone arriving in Queensland from Vietnam, the Philippines, South Korea, India, or parts of sub-Saharan Africa, the concept of deliberately adding a mineral compound to public drinking water may be genuinely unfamiliar. In some source countries, public mistrust of government water management is well founded — grounded in lived experience of infrastructure failures or contamination events that have nothing to do with fluoridation.
Migrant health advocates working across Brisbane and Southeast Queensland note that this background context shapes how newly arrived residents receive information about tap water. "The first question isn't always 'is it safe?' — sometimes it's 'what is this, and why is it there?'" said one community health worker who supports resettlement programs in Logan. "That's a very reasonable question. But if nobody explains it clearly, people fill the gap with whatever they can find online."
The Communication Infrastructure That Isn't There
Queensland Health publishes information about water fluoridation on its website. The Australian Dental Association maintains public-facing resources. Local councils often reference fluoridation in water quality reports. What is notably absent, however, is proactive, multilingual outreach specifically designed for communities with no prior exposure to fluoridated water systems.
A search of Queensland Health's translated health resources reveals extensive materials on topics such as immunisation, diabetes, and mental health — all available in multiple languages. Fluoridation-specific resources in languages other than English are, at best, sparse.
This is not a trivial oversight. Queensland is home to substantial communities of speakers of Mandarin, Cantonese, Arabic, Vietnamese, Tagalog, and dozens of other languages. According to the Australian Bureau of Statistics, more than one in five Queenslanders was born overseas. In certain suburbs of Brisbane, the Gold Coast, and Cairns, that proportion is considerably higher.
Community health interpreter services, when available, focus primarily on clinical encounters. A GP appointment or hospital visit may prompt a conversation about medications or procedures, but it rarely extends to explaining what comes out of the kitchen tap.
Cultural Health Beliefs and the Bottled Water Default
In the absence of clear information, many migrant households default to bottled water — not necessarily out of fear, but out of habit or uncertainty. In numerous countries of origin, tap water is not considered safe to drink without boiling or filtration. The cultural norm of treating tap water with suspicion does not automatically dissolve upon arrival in Queensland, regardless of the actual quality of the local supply.
This has practical consequences. Bottled water does not contain fluoride at therapeutic levels. Children in households that exclusively consume bottled water do not receive the passive dental health benefits that fluoridated tap water provides. For families already managing the financial pressures of resettlement, this is a compounding disadvantage — both economically and in terms of long-term oral health outcomes.
Dentists working in community health settings in areas with high migrant populations report seeing patterns of dental disease that reflect both prior exposure to non-fluoridated water and ongoing avoidance of the tap. "We see adults and children whose dental history tells a story," one Brisbane-based community dentist noted. "Sometimes that story continues here because nobody told them the tap water is actually good for their teeth."
The Anti-Fluoride Information Vacuum
Where official information is absent, other sources fill the void. Online communities, social media groups, and messaging platforms organised around shared language or national identity can become significant vectors for health misinformation. Anti-fluoridation content — which is produced in abundance in English and increasingly in other languages — circulates freely in these spaces.
For someone encountering fluoridation for the first time and searching for information in their own language, the results they find may skew heavily toward scepticism or alarm. Without a credible, culturally appropriate counter-narrative available in accessible language, that scepticism can become entrenched.
Migrant health advocates are clear that the solution is not simply to produce translated versions of existing English-language materials. Effective health communication requires cultural adaptation, not just linguistic translation. The framing, the tone, the choice of examples — all of these must be considered for each community.
What Genuine Inclusion Would Look Like
Several community health organisations operating in Queensland have called for a more deliberate approach to fluoridation communication with culturally and linguistically diverse communities. Their recommendations tend to converge on a few key points.
First, proactive outreach through trusted community intermediaries — including community health workers, religious leaders, and cultural associations — is more effective than passive web-based resources. Second, multilingual materials should be developed with input from community members, not simply translated by external agencies. Third, settlement services and new-arrival programs represent a natural point of contact where basic information about Queensland's water supply could be routinely provided.
None of this is beyond the capacity of existing public health infrastructure. It requires prioritisation and a recognition that the fluoridation conversation, as it currently exists, is conducted largely within a monolingual, culturally homogenous frame that does not reflect the Queensland of 2025.
A Public Health Program That Serves Everyone
Water fluoridation is a population-level intervention. Its benefits are distributed across the community without requiring individual action — which is precisely its strength. But that passive quality also means that people who do not understand what it is, or who actively avoid tap water, are excluded from those benefits.
For Queensland's migrant communities, the barrier is rarely hostility or irrationality. It is, far more often, simply a lack of accessible, culturally appropriate information. Addressing that gap is not a peripheral concern for fluoridation policy. It is central to the program's public health purpose.